

Every out-of-network claim your practice submits comes back with a number attached to it, and that number is rarely the one you billed. Sounds common? Worry no more, as most out-of-network physicians have a similar experience. For in-network care, reimbursement is predictable because it’s contracted in advance. However, for out-of-network (OON) billing, the initial payment is generally determined according to the plan’s reimbursement methodology and applicable federal or state requirements. Providers may not always receive enough information to understand the calculation without reviewing the remittance or requesting additional details.
That gap between what you charge and what you’re paid isn’t always legitimate. In fact, industry estimates suggest practices routinely leave more than half of earned OON revenue on the table simply because underpayments go unchallenged. Therefore, providers managing out-of-network claims must understand exactly how OON reimbursement is calculated, the tactics payers use to reduce what they owe, and what your billing team should be checking on every single claim is essential.
What Qualifies as an Out-of-Network Underpayment?
An out-of-network underpayment occurs when a payer reimburses less than the amount required under the applicable plan, payment methodology, federal requirement, state law, negotiated agreement, or payment determination.
However, a payment that is lower than the provider’s billed charge is not automatically an underpayment. The billed charge is the amount submitted by the provider, while the allowed amount is the figure the payer recognizes when calculating benefits and reimbursement. These amounts may differ substantially without necessarily indicating a processing error.
A potential underpayment exists when there is reason to believe that the payer:
- Used an incorrect reimbursement methodology
- Applied the wrong fee schedule or geographic adjustment
- Miscalculated the qualifying payment amount
- Downcoded a properly documented service
- Bundled separately payable services incorrectly
- Failed to recognize valid modifiers
- Applied incorrect patient cost sharing
- Classified the provider’s network status incorrectly
- Omitted one or more payable claim lines
- Failed to make an additional payment required by a settlement or payment determination
Providers must therefore examine how the claim was adjudicated instead of measuring underpayment solely by the difference between the billed charge and the payment received.
How Is Out-of-Network Reimbursement Calculated?
When there’s no contract setting the price, payers fall back on one of a few methodologies:
Method 1 – Usual, Customary, and Reasonable (UCR) — a benchmark based on what providers in a given geographic area typically charge for the same service. Payers often license third-party UCR databases (like FAIR Health), but which percentile they use and whether it’s applied correctly vary widely and are rarely disclosed upfront.
Method 2 – Qualifying Payment Amount (QPA) — The qualifying payment amount is generally based on the payer’s median contracted rate for the same or similar item or service in the applicable geographic region, calculated according to federal requirements.
Method 3 – Percentage of Medicare — Some payers reimburse OON claims as a multiple of the Medicare fee schedule, regardless of actual market rates.
Method 4 – State Payment Standards — Also, certain states have their own surprise-billing protections, payment standards, or dispute-resolution processes. These requirements may apply depending on the plan and claim.
Thus, before initiating a dispute, the provider should determine whether a state process controls the claim, the federal No Surprises Act, or another applicable payment arrangement. In fact, QPA-specific mechanics play a vital role here.
Why Out-of-Network Claims Are Frequently Underpaid
Underpayment on OON claims isn’t usually a single error; it’s typically one or several of these patterns stacking together. While some of the common issues that you might encounter are listed below.
1. Billed charges vs. allowed amount gaps — The billed charge represents the amount submitted by the provider, while the allowed amount is the amount recognized by the plan for benefit and payment calculations. The difference between the billed charge and allowed amount does not automatically become patient responsibility. Balance-billing rights and restrictions depend on the service, plan, applicable law, and whether surprise-billing protections apply.
2. Downcoding — Payers sometimes reduce the complexity level of a submitted code. It can be in cases like billing a Level 4 E/M visit down to a Level 3 to justify a lower payment even when documentation supports the original code. This is one of the most common and hardest-to-catch reduction tactics because it happens silently in adjudication.
3. Bundling — Services that should be reimbursed separately get grouped (bundled) into a single payment, effectively erasing the value of secondary procedures performed during the same visit.
4. Repricing through third-party vendors — Some payers use third-party vendors to evaluate or reprice out-of-network claims. Providers should review whether the repricing methodology was applied accurately or not.
5. Payment variance for identical services — It’s common to see the same CPT code, performed under near-identical circumstances, reimbursed at meaningfully different rates across claims, sometimes even from the same payer. Unexplained variance is a strong signal that a claim was processed incorrectly or is worth appealing. An unexplained variance warrants further review, although it does not by itself prove that the claim was processed incorrectly.
Warning Signs of an Out-of-Network Underpayment
It is important to comprehend that a formal denial does not always accompany potential underpayment. The claim may appear as paid and closed even though part of the expected reimbursement is missing. Thus one needs to be careful unless:
- A previously payable claim line receives no payment
- The payer substitutes a lower level procedure code
- Multiple services are combined without a clear explanation
- A modifier is ignored or removed during adjudication
- The allowed amount changes significantly for comparable claims
- The QPA appears inconsistent with the service or geographic area
- Patient cost sharing is calculated incorrectly
- The claim is processed under the wrong network status
- A negotiated settlement is not reflected in the final payment
- The payer fails to issue the additional amount required after a determination
- The remittance advice does not contain enough information to explain the adjustment
Payment variation alone does not prove an error. Changes in plan design, coding, patient benefits, service location, and dates of service may legitimately produce different payments. Thus, in out-of-network billing each variance must be reviewed in context.
How Providers Can Identify Payment Variances
You can’t dispute what you don’t measure. A basic underpayment-detection workflow thus must have:
- Establish an expected-payment benchmark using relevant plan information, historical payment data, applicable fee schedules, and other permissible reimbursement information. Compare the benchmark with the payer’s allowed amount after adjudication.
- Track allowed amount vs. billed charge as a standard field in your billing platform or spreadsheet, not just the final payment.
- Flag claims paid materially below the applicable benchmark or comparable prior payments.
- Segment by payer and CPT code so patterns specific to a payer consistently downcoding a specific service become visible instead of buried in complex OON claims.
Manual tracking works at low claim volume, but most practices find that patterns only become obvious once they’re looking at data across dozens or hundreds of claims, which is where dedicated OON billing support can be beneficial.
What to Do When an Out-of-Network Payment Is Lower Than Expected
If a claim comes back underpaid, the fix isn’t to accept it and move on; it’s to work the claim methodically, starting from:
- Pull the Explanation of Benefits (EOB) and identify exactly which methodology (UCR, QPA, Medicare multiple) the payer says it used.
- Review the remittance documentation for the allowed amount, QPA information when applicable, adjustment codes, and any disclosed payment methodology. If not, request clarification when necessary.
- Compare that number against your own benchmark data. If the claim qualifies under the No Surprises Act, you may have access to the open negotiation process and, if that fails, federal Independent Dispute Resolution (IDR).
- If it doesn’t qualify under the NSA, a standard payer appeal with benchmark documentation and medical necessity support is still your best path to recovery.
- If federal IDR does not apply, the provider should evaluate the payer’s reconsideration or appeal process, applicable state remedies, and any other available payment-dispute options.
How Open Negotiation Works
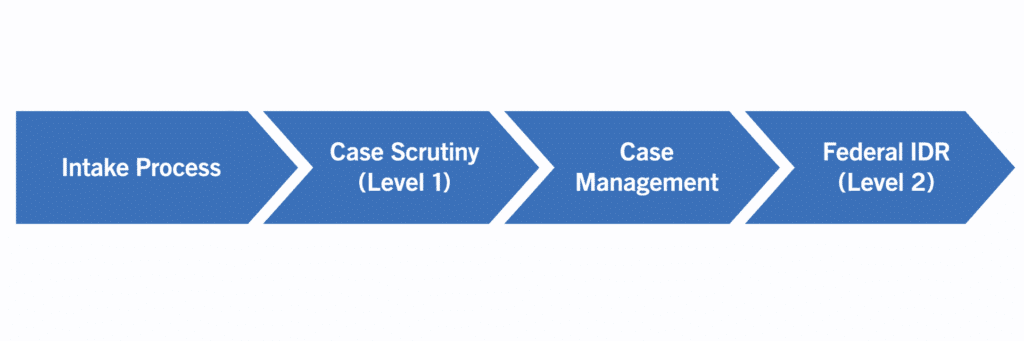
How CollectionPro Supports the Right Out-of-Network Billing
Obtaining appropriate reimbursement begins with understanding why a claim was paid below expectations and selecting the correct recovery pathway. CollectionPro supports providers throughout the process from reviewing claim and remittance information to identifying payment variances, preparing supporting evidence, managing applicable negotiation or dispute deadlines, and following the payment through collection.
Rather than challenging every low payment, we help providers prioritize claims with a defensible reimbursement issue and a reasonable opportunity for recovery.
Out-of-network underpayments are easier to control when providers combine early verification, accurate documentation, reliable payment benchmarks, and disciplined follow-up. With CollectionPro’s in-house IDR specialists supporting claim analysis, negotiation, dispute preparation, and post-determination collection, providers can strengthen their reimbursement process and reduce preventable revenue leakage.
Our goal is not to treat every payment difference as an error, but to identify genuine underpayments early, pursue them through the appropriate channel, and ensure that the final amount due is received and reconciled.
Ready to see how much your practice may be leaving on the table?
